
Safe Staffing Programme End of Year Report 25/26
Executive summary
Context and purpose of the report
In December 2025, Blake Stevenson Ltd was commissioned to support the Care Inspectorate’s Safe Staffing Programme (SSP) and produce an end-of-year report reviewing how the Health and Care (Staffing) (Scotland) Act 2019 (HCSA) continues to be embedded in everyday practice. The Act came into force in April 2024 and establishes a statutory basis for ensuring appropriate staffing, emphasising needs-led decision-making and professional judgement rather than prescribed minimum staffing numbers, with ratios applying in registered children’s day care settings.
This report provides an evidence-led account of SSP delivery during 2025/26, drawing on an external stakeholder survey, a Care Inspectorate staff survey, group discussions with Care Inspectorate teams and a structured review of programme evidence.
SSP delivery and reach
The SSP was established in 2019 to support implementation of the Act across care services and to provide accessible information, guidance, and support to a wide range of stakeholders, including Scottish Government, representative organisations, care providers, local authorities (LAs), integration authorities (IAs), and Care Inspectorate staff.
SSP delivery in 2025/26 combined high-volume activity with a small specialist team and a mix of communications, direct engagement, and targeted analytical support. SSP’s internal activity record included 790 recorded entries with activity spanning governance and reporting, stakeholder engagement, compliance/reporting exploration and review, and update of supporting guidance or resources.
Delivery is summarised under four objectives which:
ensure governance arrangements and reporting are in place, and ensure the workplan is effective and complies with legal and regulatory requirements
continue to increase stakeholder engagement using media platforms and resources to embed the HCSA into everyday practice
review and update existing supporting guidance and agree a range of core resources, which will continue to support stakeholders beyond enactment
explore how compliance with the HCSA can be reported, including opportunities to refine reporting and data collection processes within the Care Inspectorate’s existing RICE functions.
Outcomes and emerging impact
Evidence from the external stakeholder survey, internal Care Inspectorate staff survey and group discussions suggests a set of early outcomes and emerging signals of impact associated with SSP delivery during 2025/26.
For external stakeholders, confidence is generally positive and improving. Almost two-thirds reported being somewhat or very confident in implementing the Act and complying with its duties, and 45% reported their confidence had increased over the last 12 months. Where confidence increased, respondents attributed this to a mix of internal organisational work and peer learning, with SSP support also cited as a contributing factor. A consistent theme was the practical question of how best to evidence implementation. This highlighted a valuable opportunity to develop additional examples, prompts, and proportionate guidance to support colleagues in applying the Act with increased confidence.
For Care Inspectorate staff, the internal survey indicates that SSP resources are being used as day-to-day working tools and are supporting capability and consistency. Staff used the Hub and guidance materials, and around three-quarters agreed that SSP support refreshed their knowledge and contributed to their effectiveness in role. Two-thirds agreed SSP support helped them have more effective conversations with providers, and almost three-quarters agreed it improved consistency of messaging across teams. Qualitative discussions highlighted that this is most visible in the quality of conversations about needs-led safe staffing and in the prominence given to staff wellbeing within staffing decision-making.
Together, the evidence points to emerging impact through clearer understanding, stronger signposting, and more confident, evidence-informed discussions, while recognising that workforce constraints and uncertainty around evidencing continue to shape what is feasible in practice.
Key challenges and learning
The evidence review shows that both structural and contextual factors are affecting how the Act is being put into practice. Workforce pressures such as difficulties recruiting staff and ongoing shortages are limiting what some services can realistically do.
There are also important differences between service types and local contexts. This includes varying views on what “appropriate staffing” looks like and how it should be demonstrated.
A strong theme from the external survey is uncertainty about what good, proportionate evidence looks like in day‑to‑day practice. Stakeholders have asked for clearer signposting, practical examples, and simple prompts or checklists to help guide them. Examples are available in the Care Inspectorate’s quality frameworks.
Experience from delivery shows that the SSP works best when it provides practical support. This includes clear guidance, easy‑to‑use formats, responsive help, and straightforward routes to relevant materials, along with improved sector‑specific signposting.
Learning, legacy work, and future considerations
Looking ahead, confirmation of the SSP’s final transitional year provides an opportunity to maintain and refresh the programme’s legacy resources and outputs. We will continue to offer proportionate support to LAs and IAs in relation to reporting requirements. Key priorities include refining guidance and reporting prompts to improve clarity and consistency. We will also use annual returns and other intelligence to target analytical insight. Our aim is to ensure that future reporting cycles make effective use of available data without increasing the reporting burden.
The Ministerial report provides a comprehensive summary and analysis of the annual reporting findings. It is supported by Care Inspectorate data, which highlights progress made, areas of success, and priorities for further development. Together, this information shows how the Act is being implemented across Scotland’s registered care services.
1. Introduction
1.1 In December 2025, Blake Stevenson Ltd, an independent social research company, was externally commissioned to support the Care Inspectorate’s Safe Staffing Programme (SSP) to produce an end-of-year report to review how the Health and Care (Staffing) (Scotland) Act 2019 (the Act; HCSA) continues to be embedded in everyday practice.
1.2 The Act came into force in April 2024. It establishes a statutory basis for ensuring appropriate staffing in health and social care services with the aim of enabling safe, high-quality care and good outcomes for people experiencing care. This is embedded in the Act’s guiding principles with specific duties placed on care service providers, Local and Integration Authorities.
1.3 A core feature of the Act is that it does not prescribe minimum staffing levels. The Act strengthens existing local and national workforce planning by promoting a rigorous, evidence-based approach to decisions about staffing, service models, and redesign. It does not set mandatory staffing numbers, but instead supports local decision-making based on context, need, and professional judgement, with a focus on openness and transparency in staffing decisions and on staff being able to raise concerns. Minimum adult to child ratios are applied to registered children’s day care settings including school age childcare and childminders.
1.4 Within care services, the Act operates alongside existing regulatory requirements, reinforcing a culture where staffing is understood holistically as the right people, with the right skills, in the right place, at the right time. Staff wellbeing is positioned as a core component of safe, person-centred care. This is the first time there has been a legislative basis between staff's wellbeing and people outcomes with mechanisms for assessing and responding to staff wellbeing as it relates to the guiding principles in the Act. Implementation of the Act is also taking place in a challenging workforce context across parts of the sector, which shapes what is feasible for services even where understanding and intent are present.
1.5 The SSP was established in 2019 to support implementation of the Act across care services and to provide accessible information, guidance, and support to a wide range of stakeholders, including Scottish Government, representative organisations, care providers, LAs, IAs, and Care Inspectorate staff.
1.6 Within the Care Inspectorate, the SSP sits across the Directorate for Assurance and Improvement, helping to:
support consistent understanding of the Act and its duties
develop and update practical resources that can be used by stakeholders, services, and inspectors
gather and analyse intelligence to inform reporting, learning, improvements, and targeted support.
1.7 The SSP was delivered by a small, specialist team within the Care Inspectorate. For part of the year the team operated with four staff (the senior improvement advisor moved to another internal position in December 2025). From December 2025 to March 2026, it comprised a senior safe staffing advisor with regulatory experience and detailed knowledge of the Act, an improvement support officer, and an information analyst. The information analyst role is jointly linked to the Care Inspectorate’s Digital and Data Directorate, providing analytical expertise to support compliance monitoring, reporting, and data-informed decision making.
1.8 This report provides an evidence-led account of SSP delivery during 2025/26. It covers:
• SSP activity, outputs, and reach
• outcomes and emerging impact for providers/partners and for Care Inspectorate staff
• key challenges, constraints, and learning
• the legacy resources and considerations during the SSP’s final transitional year
1.9 A mixed-methods approach was used to capture both the breadth of SSP reach and delivery, through surveys and programme data, and the depth of experience and emerging learning, through group discussions and a review of programme evidence.

1.10 An online survey was used to gather perspectives from providers and partners on their awareness and use of SSP support, their confidence implementing and complying with the Act’s duties, what helps implementation in practice, what risks or barriers are most significant, and areas where clearer guidance is needed. The survey was distributed through Care Inspectorate provider updates and emailed to approximately 800 individual contacts on the SSP distribution list.
1.11 The survey was live for four weeks and there were 219 responses, with respondents from all 31 HSCP areas. The responses were spread across sectors, with the largest groups from LAs/IAs/HSCP (88), independent/private providers (77) and the third sector/voluntary/not for profit (47).
1.12 An online survey also sought the perspectives of Care Inspectorate staff on use and usefulness of SSP resources and support, confidence applying the Act in role, the extent to which SSP has supported consistency of messaging and more effective conversations with providers, and where staff would value further support. The internal survey, which was live for four weeks, received 39 responses, predominantly from inspectors (31), then team managers (7), and one corporate respondent. Respondents worked mainly in adult services (27), as well as early learning and childcare (ELC) (6) and children and young people (CYP) (4) and were mostly based in the West (18) and the North (7).
1.13 To add depth to the survey evidence, group discussions were held with Care Inspectorate teams. Nine sessions were held, involving 19 participants from teams across adult, ELC, CYP, and internal functions of complaints and registration.
1.14 To ensure the report reflects the full breadth of SSP delivery, we undertook a structured review of secondary programme evidence, including:
SSP action records and delivery logs
usage statistics for SSP resources
annual return data relevant to staffing methods and the staffing method framework (SMF)
statutory reporting materials and associated analysis outputs.
1.15 Quantitative survey data were analysed using descriptive statistics to identify overall patterns and variation across settings and roles. Open-text survey responses and group discussion outputs were analysed thematically to identify recurring themes, areas of alignment, and differences across sectors and functions. Secondary data were used to provide contextual evidence of delivery, reach, and scale of SSP activity. Findings are presented in the report using a triangulated approach, with survey findings supported by qualitative explanation and delivery evidence where relevant.
1.16 As with all mixed-methods reviews, some limitations should be noted. Participation in the research was voluntary, and survey respondents and discussion participants are likely to include those more engaged with SSP support.
1.17 Some elements of SSP support are relevant for particular contexts or settings e.g. the SMF is designed for adult care homes, so any interpretation of the findings needs to reflect this variation. Also, secondary data on activity and usage provide indicators of volume and reach, but they do not demonstrate changes in practice and so are used as delivery evidence and triangulation.
1.18 Even with these challenges, the combined approach provides a basis for describing SSP delivery and identifying outcomes, emerging signs of impact, and practical learning.
1.19 The remainder of this report is structured as follows:
• chapter 2: SSP delivery and reach
• chapter 3: Outcomes and emerging impact
• chapter 4: Key challenges and learning
• chapter 5: Learning, legacy resources, and future considerations.
2. SSP delivery and reach
2.1 This chapter sets out what the SSP delivered during 2025/26. It highlights the volume of activity and the depth of work involved in supporting stakeholders to interpret the Act in practice, maintaining and refreshing legacy resources, and producing internal and external reporting and analysis that underpins assurance and improvement activity
2.2 The SSP’s internal activity record shows a sustained level of delivery across the year, with 837 recorded entries for the period 1 April 2025 to 31 March 2026. The record also shows delivery spread across the SSP team objectives with activity against:
• governance arrangements and reporting (214)
• stakeholder engagement (179)
• review and update of supporting guidance and resources (83)
• compliance/reporting exploration (127)
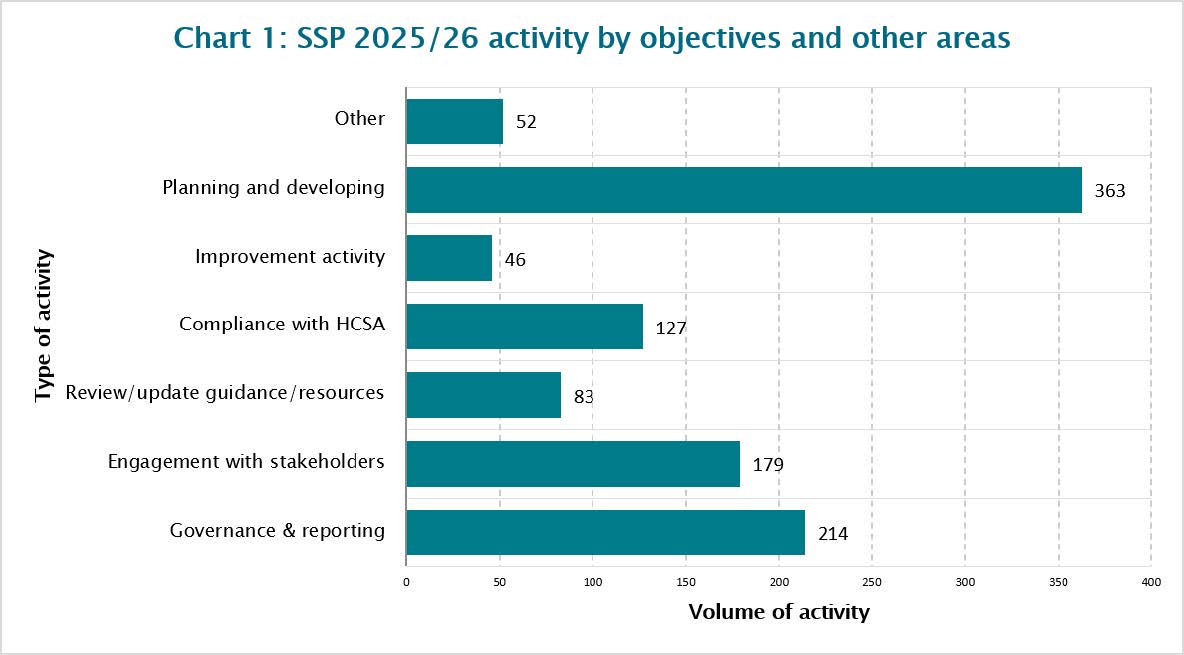
2.3 The largest category in the activity record, Other, captures the behind-the-scenes activity required to deliver SSP support.” This includes day-to-day planning and coordination, preparation for sessions and presentations, follow-up and administration linked to meetings, completion of programme recording or forms, and development work linked to reporting outputs like end-of-year report activity and internal learning assets e.g. training materials.
2.4 These categories highlight the significant effort required to maintain credible, accurate implementation support.
2.5 To provide an account of the breadth of delivery, we have summarised SSP activity under four workstreams and set out what was delivered and how this reached stakeholders.
2.6 Workstream 1 covers SSP’s communications and knowledge-building activity during 2025/26. This workstream is central to the SSP’s ability to reach a wide and diverse set of stakeholders efficiently and to provide information that can be easily accessed. Across the year, the SSP maintained and refreshed a set of core communication channels and continued to develop and update resources in multiple formats to support different learning preferences and levels of digital confidence. The SSP’s communications activity focused on maintaining a clear and accessible information offer, which included:
• newsletters and updates, supporting regular dissemination of key messages and signposting to a distribution list of 818 recipients
• Hub-based information and signposting, including sector-specific Hub pages and a suite of resources such as FAQs, information guides and supporting materials
• recorded webinar content and short learning formats, enabling stakeholders who cannot attend live sessions to access learning and refreshers at a time that suits them
• podcasts providing an alternative route to learning and sharing ley messages in an accessible format
• internal communications and reference products including inspector and team manager resources to support consistent statutory referencing and messaging
Data shows the reach of the SSP communications and resource channels. During the reporting period:

2.7 Usage data provides an indication of the reach of SSP’s communications and on-demand resource channels across the reporting period. The infographic below summarises headline activity across Hub pages, recorded webinars, bite-size videos, and podcasts.
2.8 These usage data indicate that the SSP’s resources are being accessed repeatedly and in different formats, supporting implementation through both external and internal on-demand routes. Findings on stakeholder experience of these channels are presented in Chapter 3.
2.9 Workstream 2 captures the SSP’s direct engagement and advice to help stakeholders to understand and apply the Act in everyday practice. Across 2025/26, the SSP provided a mix of interactive activities open to all stakeholders, targeted sessions for specific partnerships or groups, and additional follow-up input where services required more practical help. This is reflected in the SSP’s internal recording, with a substantial volume of activity logged under stakeholder engagement alongside the coordination and follow-up needed to provide consistent, timely support.
2.10 The SSP’s engagement and implementation support included:
• interactive engagement sessions like webinars and online sessions to explain duties, respond to frequent questions, and support consistent understanding
• targeted partnership sessions where the SSP delivered tailored input for local areas or groups of providers e.g. delivering sessions in response to partnership needs and supporting providers experiencing difficulties
• advice and follow-up support, including practical input to help services work through staffing questions, evidence expectations, and the use of methods or tools where relevant.
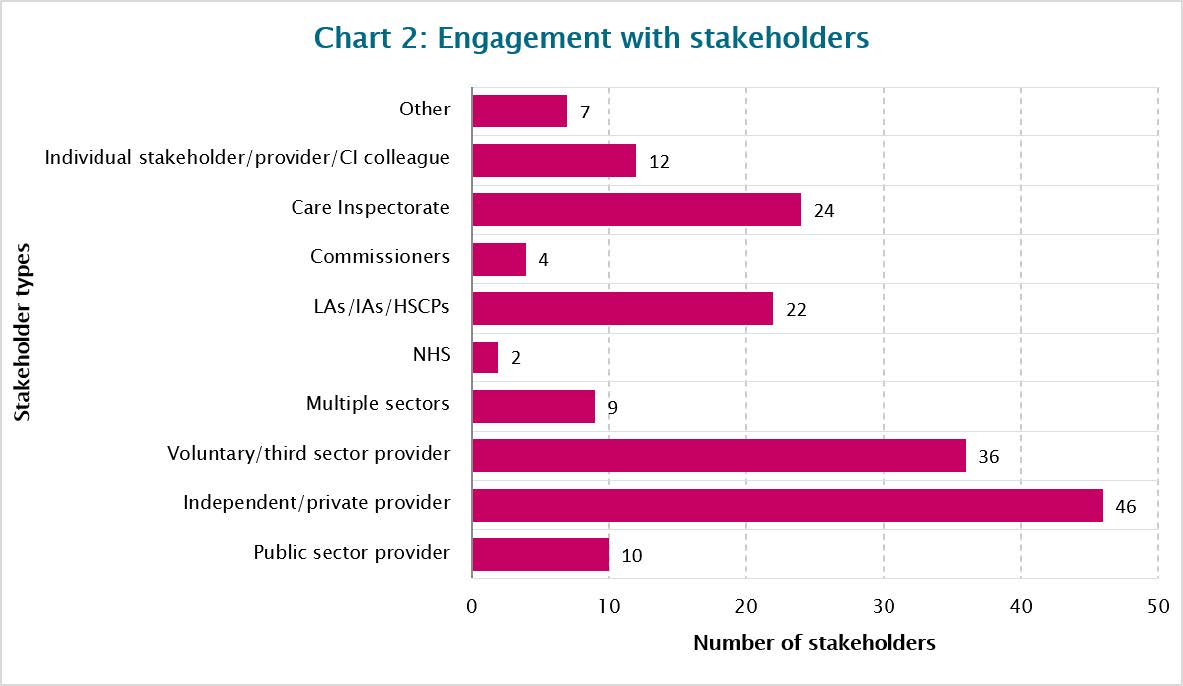
2.11 Workstream 2 delivery reached a broad mix of stakeholders and settings. SSP activity data indicates wide geographic coverage across all HSCP/LA areas, reflecting multi-area and multi-system engagement consistent with a national programme supporting implementation across different service contexts.
2.12 The chart shows the range of stakeholders supported, based on the team’s activity logs between April 2025 and March 2026.
2.13 The external stakeholder survey shows that live engagement is a core route through which stakeholders experience the SSP. Nearly half of the respondents reported attending webinars or online sessions in the last 12 months.
2.14 The same core questions about how to implement the guidance in everyday practice arose across the sessions and follow‑up support. People wanted reassurance that “appropriate staffing” is based on the needs of the service and not a fixed number of staff (except in children’s day care, school age childcare and childminders, where set ratios apply).
2.15 They also looked for practical examples of what proportionate evidence looks like in everyday practice, what to record, what to show, and how much is enough.
2.16 There was also a strong focus on having more informed conversations about whether staffing is sufficient, including how staffing tools and methods can help. Throughout, the SSP emphasised that staff wellbeing is a key part of safe staffing decisions and should be considered alongside staffing levels, deployment, and training.
2.17 Workstream 3 covers the SSP’s work to support understanding and appropriate use of staffing methods, including the SMF, which is intended for use in adult care home contexts but has some transferability to other sectors.
2.18 Providers and stakeholders continue to look for clear answers on what appropriate staffing looks like. The SSP’s role has been to signpost and explain available approaches, support more structured conversations about staffing sufficiency, and help staff and services move away from the expectation that there should be a single dependency tool or prescribed staffing number.
2.19 In 2025/26, the SSP’s staffing methods support included:
• maintaining and signposting SMF resources and links through the Hub/Right Decision Service, ensuring stakeholders and staff could access the SMF and associated information when needed
using the SMF as a practical conversation support in adult service contexts by helping Care Inspectorate staff to use it in evidence-based discussions with providers, reinforcing that staffing decisions should be based on needs and outcomes
• highlighting the importance of professional judgement with accumulated knowledge, skills, experience, and reasoning by qualified staff to make informed, evidence-based decisions, particularly in complex or uncertain staffing situations. Under the HCSA, professional judgement is crucial for determining safe staffing levels and ensuring quality care, in partnership with other health and social care professionals, residents, staff, and their families.
2.20 While the activity log provides evidence of SMF-related resource signposting and related support functions, much of Workstream 3 is best evidenced through how staff describe using the SMF and discussing alternatives as part of provider interactions.
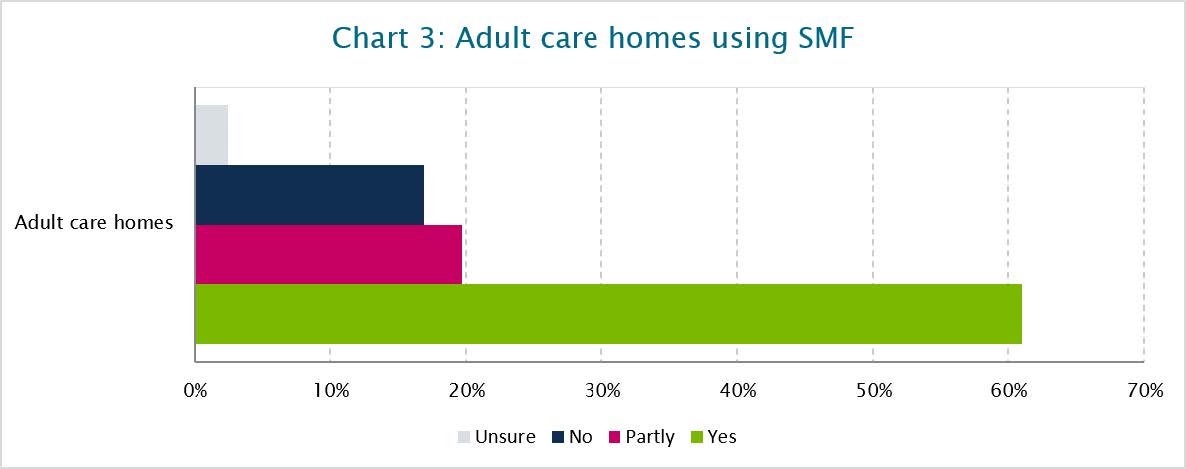
2.21 Evidence from the external survey provides important context on reach and relevance. The SMF is designed for use in adult care home contexts. In the external survey, 28 respondents were from care home services for adults and older people, while 33 respondents said they were using the SMF or parts of it.
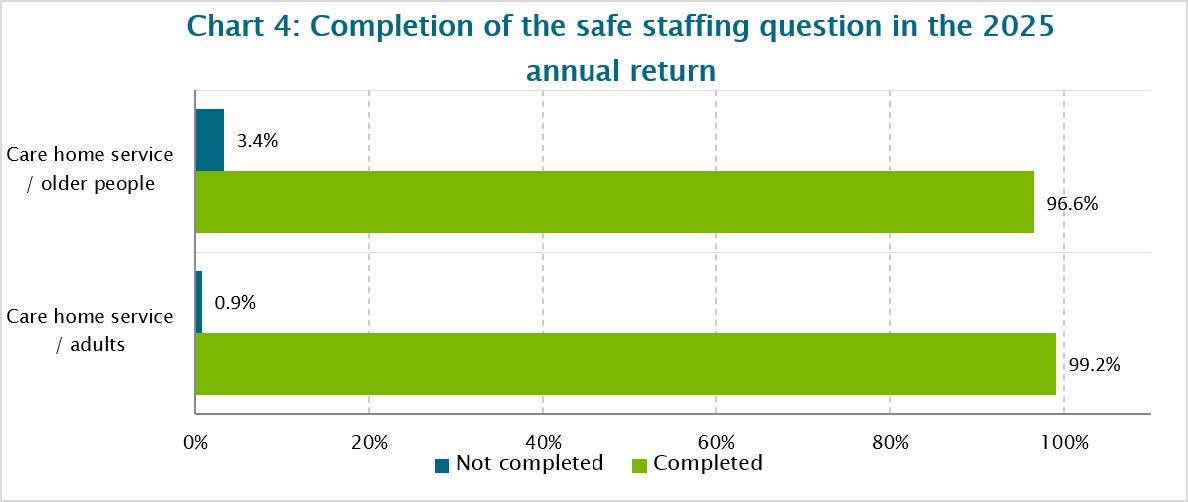
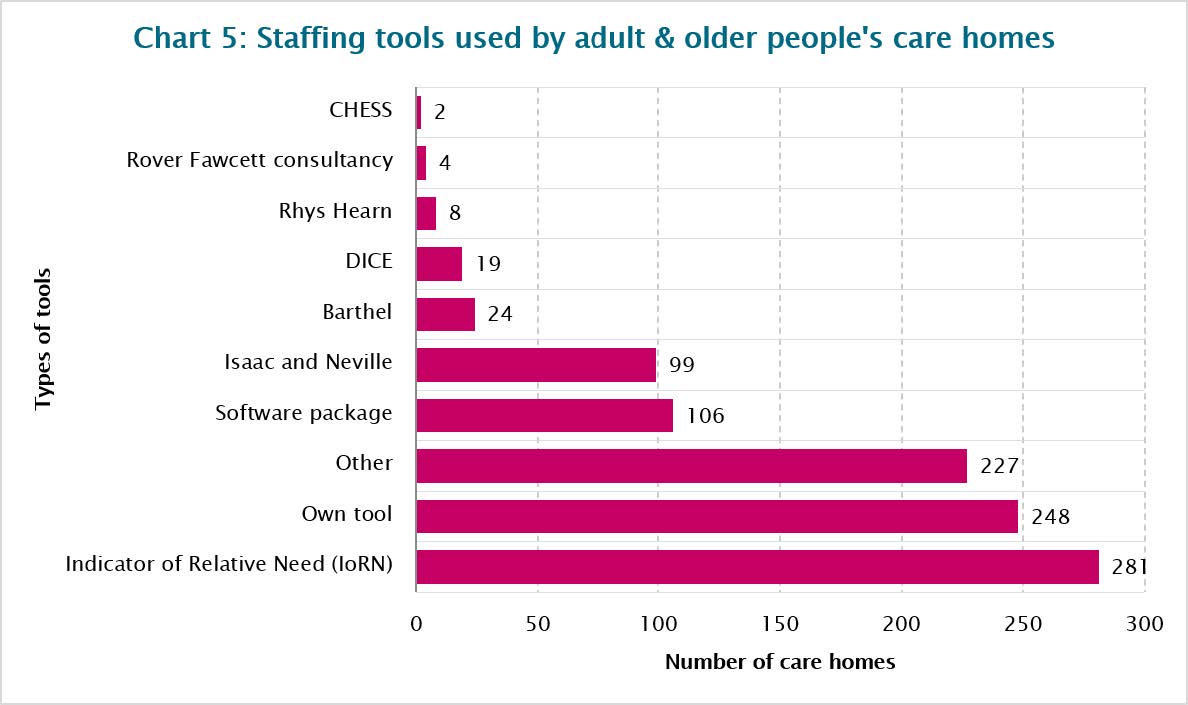
2.22 The Care Inspectorate’s annual return module provides a snapshot of staffing methods and tools in use in adult care homes, including reported use of the SMF and the balance between numerical workload information and professional judgement in staffing decisions.
2.23 As of 31 December 2025, 972 of 1,000 registered adult care homes completed the staffing methods/tools section. Completion was 99.1% for adult care homes (233 of 235) and 96.6% for older people care homes (739 of 765).
2.24 Annual return data also shows that within the 972 adult care homes that completed the section, 593 services (61.0%) reported using the SMF and a further 191 (19.7%) reported using it partly.
2.25 This annual dataset indicates that 884 of 972 services (90.9%) reported using formal staffing tools when assessing and reviewing staffing levels, compared with 85.4% in the previous year, suggesting a growing use of structured approaches even where specific tools and levels of SMF use vary.
2.26 This workstream covers the SSP’s monitoring, intelligence, reporting, and compliance-related activity during 2025/26. This strand is a significant part of SSP delivery and underpins both internal assurance activity and national reporting requirements. It includes routine intelligence gathering across multiple Care Inspectorate evidence sources and dedicated support to LAs and IAs for their reporting duties and analysis that fed into the Health and Care Staffing Annual Report for Ministers.
2.27 This workstream helps ensure that SSP support and messaging are informed by evidence. It also enables the Care Inspectorate and Scottish Government to draw on structured information about implementation, emerging risks and learning from the first cycle of statutory reporting by LAs and IAs.
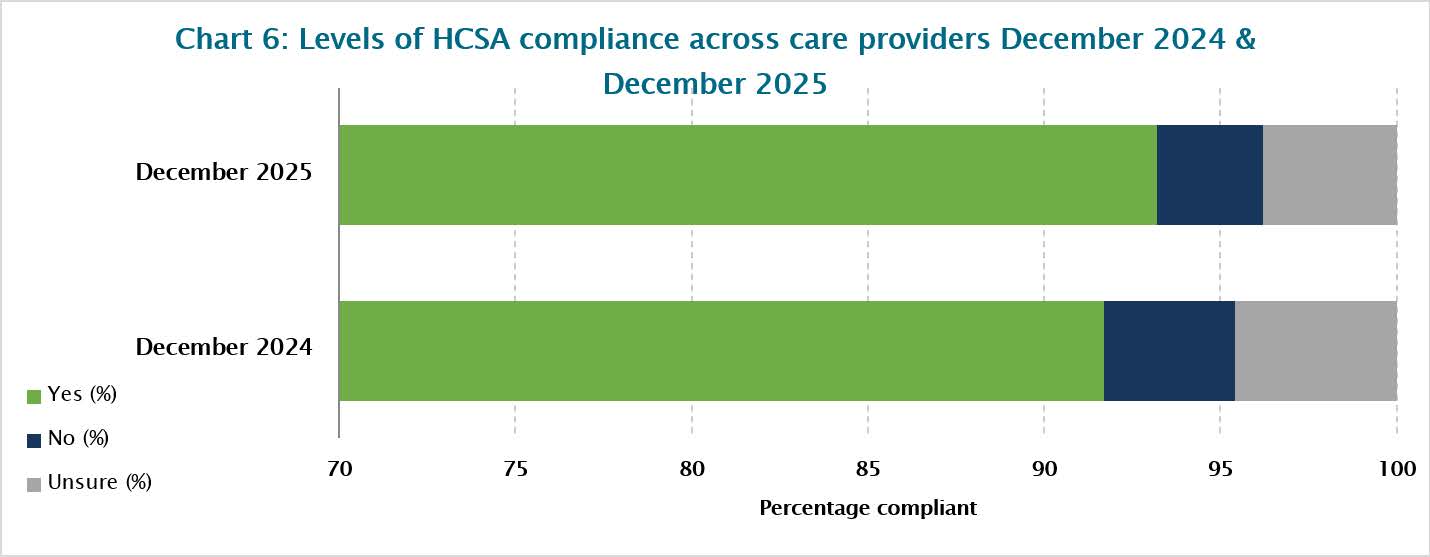
2.28 The HCSA places a duty on LAs and IAs to report annually on how they have met their responsibilities when planning or securing care services from a third party, including any ongoing risks to compliance. These reports must be submitted to Scottish Government by 30 June each year. Scottish Ministers then consider the information provided and lay a Ministerial report before the Scottish Parliament.
2.29 The purpose of the annual reporting requirement exists to:
• promote transparency about how decisions on staffing are made when services are commissioned
• demonstrate accountability for ensuring that commissioned services are planned in line with safe‑staffing principles
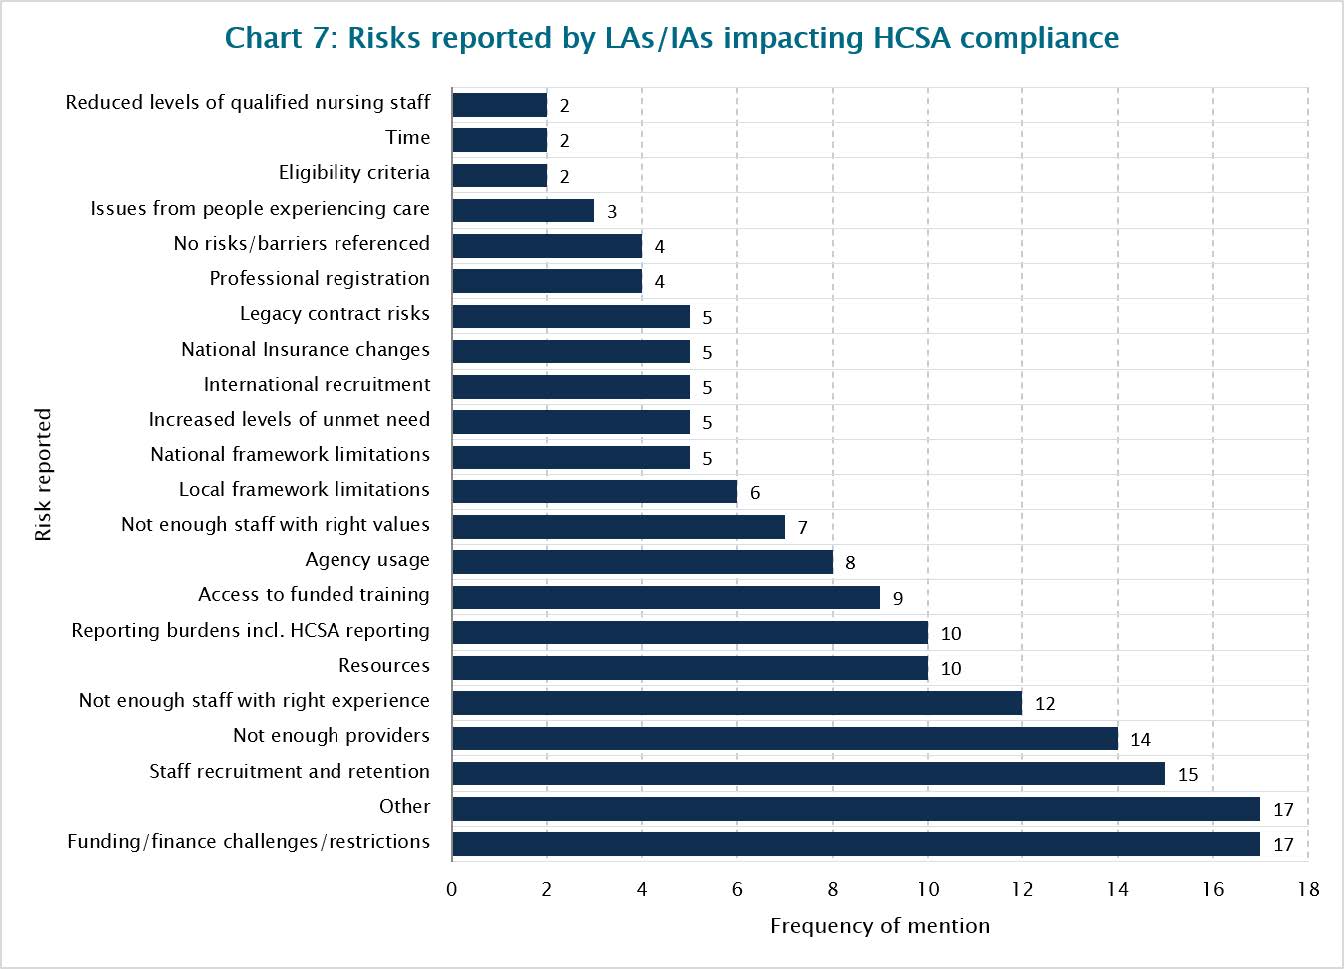
• highlight risks, such as workforce shortages or commissioning challenges that could affect safe care, early
• support national oversight, allowing Scottish Ministers to review the information and respond at a system level.
2.30 Scottish Ministers have obligations under the Act to present these reports to Parliament and explain what actions they will take to ensure the availability of funding, and sufficient numbers of staff to support the discharge of HCSA duties as well as determine the future supply of care professionals. The First Ministerial Report for the Health and Care (Staffing) (Scotland) Act 2019 (the Act) was published on 27 November 2025.
2.31 The SSP provided sustained support to the first reporting cycle during 2025/26. This is captured within the SSP’s activity recording, including a specific logged activity category for LA/IA HCSA reporting duties and a wider set of activity recorded under LA and IA support.
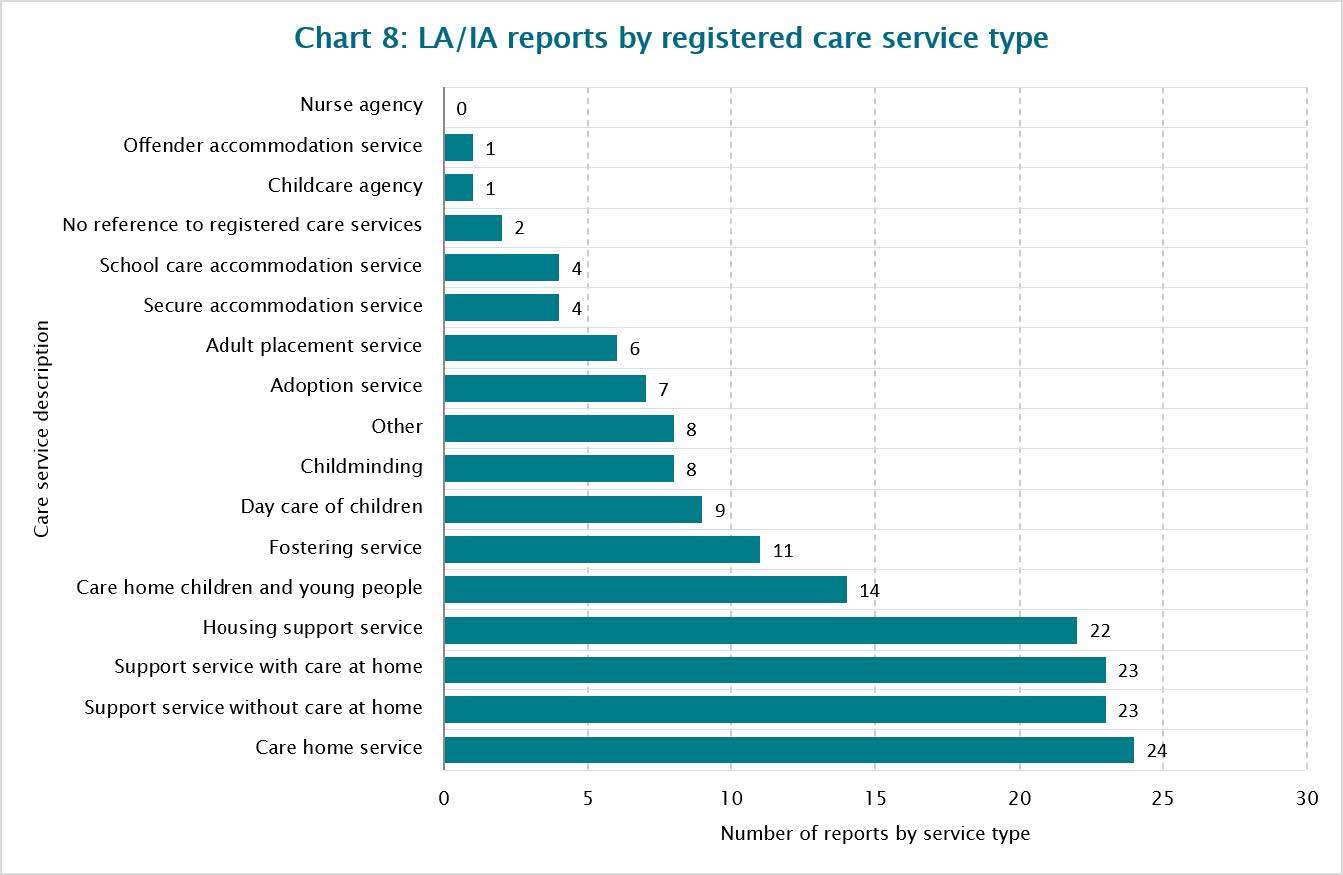
2.32 Importantly the log shows that this was not one-off queries, it includes discrete entries relating to review, collation, and comparative analysis of LA/IA reports.
2.33 SSP support for the first HCSA reporting cycle focused on helping LAs and IAs understand the reporting template questions and the types of information expected.
2.34 They also handled questions and requests for support linked to the reporting duty and associated implementation issues, including signposting to relevant guidance and resources where appropriate. In addition, the team helped improve the clarity and reduce ambiguity of report content so that local activity and learning are more visible at national level.
2.35 Alongside the LA/IA reporting work, the SSP maintained a structured programme of intelligence gathering and analysis across the year. The SSP recorded routine data mining activity across 2025/26 that drew on multiple internal evidence sources. Alongside the annual returns data, these sources were staffing-related requirements, staffing-related enforcement, complaints, areas for improvement, and staffing-related notifications.
2.36 The recurring issues identified in inspection reports reviewed by the SSP team tended to centre on the same themes: whether staffing levels met assessed need, whether staffing decisions were well‑evidenced and regularly reviewed, and whether services had the skills, training, and support required to deliver safe, high‑quality care. Because this data was only produced when staffing quality indicators were selected during an inspection, the insights reflected patterns from those inspections rather than a full system‑wide picture.
2.37 Staffing-related requirements: These issues commonly focused on whether services had sufficient staff and whether staffing was deployed in a way that consistently met people’s assessed and changing needs. They related to how services determined their staffing levels and how clearly they could explain the rationale behind these decisions. In practice, this highlighted the need to strengthen leadership, improve skill mix and experience, enhance induction and supervision, and address staff wellbeing where workload pressures were affecting safe and reliable care. There was also a need to strengthen governance and management oversight of staffing decisions, improve documentation to ensure assessments and decisions were clear, and enhance workforce planning. This included better planning, completion, and monitoring of staff registration and training, as well as robust contingency arrangements for vacancies and staff absence, including the safe and effective use of agency staff.
2.38 Staffing-related enforcement activity: This typically reflects situations where staffing, training, or supervision deficits are persistent and create or sustain risk that cannot be mitigated through routine improvement activity alone. This can include circumstances where understaffing contributes to repeated shortfalls in care, where staffing arrangements are unsafe, or where there is a pattern of not responding effectively to known staffing risks over time. In these circumstances, staffing is often interlinked with wider weaknesses in leadership, oversight, risk management, and the ability to maintain safe systems of delivery. 2.39 Complaints data: This can highlight the ways staffing pressures are experienced by people using services and their families. This often includes missed or late visits, delays in response, and concerns about personal care not being delivered properly or with dignity where time pressures are acute. Complaints may also reflect challenges around continuity and communication, where high workload and staff turnover contribute to inconsistent experiences. In care home contexts, concerns about reduced meaningful activity or engagement can also feature where staffing capacity is constrained.
2.40 Staffing-related notifications: These can provide early signals of acute pressure or emerging risk. Examples include notifications indicating service disruption due to staffing shortfalls, notifications where staffing capacity contributes to delays in responding to incidents, and notifications suggesting exceptionally high reliance on agency or unstable staffing arrangements. Notifications can help identify periods of heightened pressure and where additional support, scrutiny, or clarification may be required.
2.41 Taken together, Workstream 4 enables the SSP to support statutory reporting cycles and contribute to the evidence base that informs organisational/sector synthesis and learning. It maintains an ongoing view of emerging staffing-related issues across multiple Care Inspectorate evidence streams, strengthening internal assurance intelligence. It also helps to inform and refine SSP resources and communications so that support responds to evidenced patterns and recurring questions.
2.42 Across 2025/26, SSP delivery combined:
• high-volume, sustained activity across the year, with delivery spread across the SSP team
• a core programme of engagement and implementation support;
• a maintained set of resources and learning products used routinely by Care Inspectorate staff as practical tools
• sustained investment in monitoring, intelligence, reporting and compliance-related analysis, including local/integration authority reporting support and outputs that contribute to Care Inspectorate and Scottish Government reporting needs.
3. Outcomes and emerging impact
3.1 This chapter summarises outcomes and early signals of impact associated with SSP delivery during 2025/26. It draws on the external stakeholder survey, the internal Care Inspectorate staff survey, and qualitative evidence from the nine group discussions. Throughout this chapter, we use full verbatim quotes from the survey responses and the discussion notes to illustrate key themes.
3.2 Across the evidence base, four key messages emerged.
• The SSP’s core communication and engagement channels are widely used and perceived as useful although a minority of external stakeholders are still to engage with the support, reinforcing the importance of proactive signposting.
• Confidence implementing and complying with the Act is broadly positive, but implementation remains constrained by workforce pressures and by uncertainty about what proportionate evidence looks like in day-to-day practice.
• For Care Inspectorate staff, SSP support is associated with refreshed knowledge, greater effectiveness in role, and more effective conversations with providers, supported by practical resources and access to specialist input.
• More confident and evidence-informed conversations about safe staffing, create clearer understanding of expectations, and stronger signposting to resources.
Awareness and use of SSP support
3.3 External survey results provide evidence on how the SSP is experienced. Of the 219 respondents, 88 (40%) reported using newsletters or provider updates and 72 (33%) reported using the Hub/web pages/resources. These findings support the Hub and updates as key routes for awareness-raising and on-demand access, with webinars/online sessions also widely used and most often accessed (102; 47%).
3.4 A minority of respondents (24%) reported no engagement with SSP support over the last 12 months. Stakeholder comments show that where resources are used, they are valued, because they are easy to access and applicable to practice. At the same time, comments reinforced the continuing importance of visibility and navigation.
“Easier way to search for documents related to our sector.” - Provider
3.5 Care Inspectorate staff described signposting to the Hub as routine and noted that providers often find resources helpful once they know they exist. They also noted that some providers are reluctant to admit uncertainty, which can reduce the likelihood of seeking support.
“Further signposting from the relevant regulatory bodies and support networks.” - Provider
3.6 When asked which support was most useful, webinars and online sessions were most frequently selected (52; 24%), followed by the Hub/web resources (37; 17%) and newsletters/provider updates (26; 12%). Comments explained why the interactive sessions were valued.
“Positive opportunity to ask questions, share information, etc.” Provider
3.7 Another respondent described the usefulness of the webinars.
“This is where we learner all about the framework, we were given a task to do which we then replicated back in the setting.” Provider
3.8 Survey responses show a positive confidence picture in both implementing the Act into everyday practice and complying with its duties, with 138 respondents (63%) saying they were somewhat or very confident. Respondents also report confidence improving over time, with 98 (45%) reporting increased confidence over the last 12 months. Where respondents reported increased confidence, they identified a combination of influences, including internal organisational work and peer learning, alongside SSP support.
3.9 Qualitative evidence helps explain why confidence can improve overall while uncertainty persists in specific areas. Care Inspectorate staff discussions described a recurring expectation among providers in adult care settings that they would prefer to be told the “right number” of staff to deploy. This reflects the ongoing transition from a ”fixed number” mindset towards needs-led, contextual decision-making and evidencing rather than a minimum ratio (like in childcare settings) or dependency tool.
3.10 External survey responses provide a clear picture of what stakeholders view as the most important practical enablers - clear guidance and communication, training and professional development, supportive management and/or peer support, and structured tools.
3.11 These enablers are linked to the risks respondents face, which are dominated by workforce pressures – recruitment challenges and staff shortages, staff costs, deployment of staff, time to train staff, and staff wellbeing. Care Inspectorate discussions highlighted the importance of this context.
“The Act arrived into an environment of immense staffing pressure.” Care Inspectorate staff
3.12 The discussions described the Act coming into force in an environment where workforce pressures shape what is feasible, therefore progress can be incremental.
3.13 In the external survey, clarity on what to record or evidence was mixed, with 69 respondents (32%) not sure,68 (32%) quite clear, and 36 (17%) very clear. A further 42 (20%) reported low clarity (19; 9% not very clear and 23; 11% not at all clear). The open-text responses are consistent with the type of support stakeholders are seeking - practical examples, clearer guidance, and simple prompts or checklists. Care Inspectorate staff discussions echoed this, with staff describing providers seeking clarity on what is expected.
3.14 The SMF is for use in adult care home contexts. In the external survey, all 33 adult care service providers reported using the SMF, or parts of it. Among these respondents, the SMF is described as a way to bring structure to staffing decisions and related conversations, supporting a needs-led approach and helping with workload planning and deployment.
3.15 Respondents also highlighted the value of the SMF in reinforcing risk management and the need to evidence how staffing decisions were reached, as well as helping them consider local factors such as work environment and locality. This suggests that where the SMF is used, it is valued as a practical framework for structured judgement and evidence.
3.16 This is supported by feedback from Care Inspectorate staff in the group discussions, who described the SMF as supporting more qualitative, evidence-based conversations than older dependency tools.
“Previously we had dependency tools…deficit focused…it’s more qualitative now as well.” Care Inspectorate staff
Practical usefulness of SSP products and channels
3.17 The internal staff survey shows that SSP support is being used routinely, particularly the Hub and guidance materials, alongside tools to support signposting and practice, induction inputs, and recorded learning products. In the internal survey, staff most frequently reported using the SSP Hub (27 out of 39; 69%) and guidance materials or signposting (20; 51%). Alongside this, provider/LA/IA guidance tools (16; 41%), induction inputs (15; 39%), and recorded webinars/podcasts (11; 28%) were also used. 3.18 When asked which support was most useful, staff most often selected the SSP Hub (24; 62%), followed by guidance materials/signposting (14; 36%) and provider/LA tools (13; 33%). Internal comments illustrate why the SSP offer works for staff in practice.
“Without all of these different types of information I would not be able to provide my team with the correct knowledge and information. They also use it regularly. The team have been instrumental in supporting us to ensure we are proportionate and are able to signpost services”. Care Inspectorate Staff
3.19 These messages are reinforced in discussions, where staff described the SSP as accessible and highlighted the practical value of resources that can be used quickly while drafting requirements or preparing to engage with services.
3.20 Internal survey responses show that SSP support is associated with refreshed knowledge and increased effectiveness in role. Around three-quarters of respondents agreed that SSP support had improved or refreshed their knowledge (28; 72%) and contributed to their effectiveness in role (28; 72%). Staff also reported high confidence in evaluating compliance with HCSA duties in their role (32; 82% confident/very confident).
“The material that I can revisit – such as guidance and recorded videos/webinars – has supplemented the original training I had. The accessibility of the safe staffing team has also been useful to answer specific questions.” Care Inspectorate staff
3.21 Discussions helped explain what that looked like in practice. Staff noted SSP support helps ensure correct statutory referencing in requirements and registration contexts, and described the SSP as a specialist back-up for complex situations, including where technical input is needed to support evidence-based discussion of staffing sufficiency. One discussion summarised the overall shift in increased knowledge.
“All inspectors at this stage are definitely a lot clearer about the Safe Staffing Act and the implications”. Care Inspectorate staff
3.22 Internal survey results indicate that the majority of staff believe SSP support has helped them have more effective conversations with providers and improved consistency of messaging. Two-thirds of respondents agreed that SSP support helped them have more effective provider conversations (26; 67%) and almost three-quarters agreed it improved consistency of messaging across teams/areas (28; 72%). Discussions reinforced this while noting the challenge of maintaining consistency when service settings differ and professional judgement varies. A recurring point across internal staff evidence is the practical importance of resources that support correct legislative references and consistent wording, particularly for inspection requirements and registration contexts, where precision supports clarity and consistency.
3.23 Drawing together the survey evidence and discussion insights, early signals of emerging impact are visible.
3.24 There is increasing confidence and more evidence‑informed discussion about safe staffing in social care. SSP support appears to be strengthening how LAs, IAs, and providers consider their staffing duties under the Act. Inspectors report that conversations with providers are becoming more structured and effective, with a clear shift away from relying on a fixed number of staff toward responsive, needs‑led, person‑centred decisions supported by professional judgement, in line with the duties of the Act.
3.25 Staff wellbeing has greater prominence. The discussions suggested that the Act and SSP support have helped give staff wellbeing stronger emphasis in provider conversations. This aligns with the ongoing workforce and wellbeing pressures reported by stakeholders, and the continued desire for practical supports to sustain wellbeing in real-world conditions.
3.26 There is a clearer understanding of expectations, although evidencing remains a potential barrier. While confidence is generally positive, the external survey indicates continuing uncertainty about what constitutes proportionate evidence. Stakeholders are asking for practical tools to reduce uncertainty and support consistent practice.
3.27 The evidence suggests the SSP’s core messages resonate most where resources align closely to service context (e.g. adult care home settings for the SMF), while CYP and ELC colleagues continue to seek sector-specific articulation and examples.
4. Key challenges and learning
4.1 This chapter draws together the main challenges and constraints shaping implementation during 2025/26, and the learning emerging from SSP delivery. It brings together what stakeholders and Care Inspectorate staff reported through the external and internal surveys, and the group discussions.
4.2 Key messages:
• Implementation continues to be shaped by structural workforce pressures, including recruitment or staff shortages, costs, time for training, and staff wellbeing.
• There is clear variation by setting or sector in how the Act is applied and what support is most relevant, particularly across registered care services.
• Evidencing implementation remains a persistent challenge, with some stakeholders still unsure about what constitutes HCSA compliance from the range of evidence they have available to them and seeking practical guidance, examples, and checklists.
• Learning reinforces what works and where to refine without expanding the overall offer.
Workforce pressures
4.3 The external survey provides a consistent picture of the pressures stakeholders are dealing with as they embed the Act in practice. Respondents identified risks dominated by the realities of workforce capacity: recruitment and shortages, the cost of staffing, time for training, and the impact of staffing pressures on wellbeing.
4.4 Workforce pressures are also reflected in national workforce intelligence. The Staff vacancies in care services 2024 provides data on vacancies reported by care services through annual returns to the Care Inspectorate. As at 31 December 2024, 44% of care services reported vacancies and 61% reported having problems filling vacancies, citing reasons such as few applicants in general and too few qualified applicants.
4.5 The group discussions provided the operational context - participants were explicit that the Act is being implemented in a challenging environment. This pressure presents as limited ability to implement changes quickly, particularly where services link staffing improvements to affordability.
Variation by setting and sector
4.6 A second constraint is that implementation is not experienced evenly across settings despite the fact that the new HCSA staffing and training requirements closely mirror the previous repealed Regulation 15 on staffing. Survey and discussion feedback indicates that messaging needs to be tailored, as practice context can differ across sectors.
• For adult services, staff in the adult teams repeatedly described a continuing demand for certainty, particularly a tendency for providers to seek fixed answers about numbers or tools. This is not a small communication issue; it is a fundamental point about how the Act is understood. It reinforces the need to keep returning to needs-led staffing and the importance of structured conversations that link staffing decisions to people’s needs, outcomes, and workforce wellbeing.
• For ELC, colleagues described a context dominated by workforce pressures and the need for proportionate expectations in practice. Internal feedback underlines the value of sector-specific learning that focuses on real practice. This suggests that even where the Act’s principles are accepted, how it translates into ELC reality needs to be articulated clearly and in a way that is sensitive to the constraints services face.
• For CYP, discussions emphasised that despite the flexibility offered by the HCSA, providers often frame staffing through ratios and existing assurance processes. The practical need is less about introducing new concepts and more about achieving shared internal clarity on what good looks like when using current assessment models and staff tools for workforce planning.
4.7 The survey and discussion evidence points to two connected issues within adult care homes, where the SMF is intended to provide guidance. First, there remains an expectation among some providers that there should be a prescribed single dependency tool or a minimum staffing number. Second, there is variability in how the SMF is understood and used in practice. At the same time, Care Inspectorate staff in the adult teams confirmed that when the SMF is positioned clearly and used as intended, it is valued as a more qualitative framework that supports structured, evidence-based conversations about staffing and has the potential, with strong leadership and professional judgement, to deliver on safe staffing and quality care.
4.8 A clear theme from the external survey is uncertainty about what constitutes proportionate evidence of compliance. Stakeholders are asking for clearer, simpler guidance that translates into day-to-day action and documentation.
4.9 Group discussions highlight this too, with evidencing uncertainty visible in inspection and improvement conversations and potentially compounded where providers are defensive or reluctant to admit gaps in understanding. Across the evidence base, the request is relatively consistent and practical. They want clearer articulation of what good practice looks like in different settings, examples of proportionate evidence, and practical tools like checklists or templates that help services show their reasoning and actions.
4.10 The internal staff survey and discussions highlight that the SSP’s most valued features are those that support proportionate practice, so the next phase of support is less about creating additional content and more about how existing support is packaged, signposted, and targeted. The focus could be on:
• streamlining signposting and navigation to help stakeholders find the right resource quickly, especially by service type or sector
• strengthening sector-specific resources and practical examples to support consistency and confidence
• supporting evidencing by providing checklists, guidelines, and examples of proportionate documentation
• clarifying SMF positioning so services know where it applies and the alternatives that can be used in other settings.
4.11 Overall, the evidence suggests that the main challenges to implementation are structural and contextual. So the SSP’s remaining contribution should continue to provide clear guidance, accessible formats, and responsive support while continuing to refine how resources are packaged so that staff and services can quickly identify what is relevant and what constitutes proportionate, meaningful evidence in their setting.
4.12 While many factors sit outside the SSP’s direct control, it adds value by reducing uncertainty, supporting consistency, helping services, and allowing Care Inspectorate staff to make progress within constrained conditions.
5. Learning, legacy resources, and final year considerations
5.1 This concluding chapter sets out what will remain available following 2025/26, how the existing SSP resource set will be maintained and refreshed, and the key considerations for the final transitional year of the programme. It avoids repeating chapter 4 by focusing on what the SSP can control and how learning from 2025/26 will shape the programme’s final year.
5.2 A key output of SSP work to date is the development and maintenance of a legacy resource set that supports ongoing implementation. During 2025/26, this resource set continued to be used by external stakeholders and Care Inspectorate staff, with the Care Inspectorate website and associated guidance materials consistently identified as among the most useful supports available.
5.3 The legacy resource set includes:
• SSP website pages and signposting routes
• FAQs and information guides supporting quick access to answers and consistent messaging
• tools, templates, and practice supports where available
• learning assets, including recorded webinars and podcasts, and Care Inspectorate staff learning products hosted on internal systems
• inspector/team manager requirement support resources to support consistent statutory referencing and internal confidence.
5.4 Learning from 2025/26 suggests these resources have greatest value when they are easy to find, clearly relevant, and available in usable formats. Maintenance should therefore focus on:
• refreshing and quality assuring existing content
• consolidating overlapping materials where possible
• improving signposting and navigation so stakeholders can quickly locate what is relevant for their setting
• making limited, targeted updates where evidence shows a clear need.
5.5 This emphasis aligns with stakeholder feedback on navigation and the internal staff perspective on value and usability.
5.6 It is also important to note that ongoing consideration of the HCSA duties will continue through business-as-usual inspection and assurance activity. Inspectors will manage HCSA within normal inspection conversations, requirements, and follow-up activity, drawing on the legacy resource set for signposting and consistent messaging.
5.7 Evidence from 2025/26 points to the following delivery features that should be retained because they are valued by both external stakeholders and internal staff:
• accessible channels that fit time-pressured settings
• multi-format resources, allowing staff and services to revisit learning in different ways
• practical tools that support consistency, including resources that support correct statutory referencing and consistent requirements
• responsive specialist support where needed, including practical input in more complex situations.
5.8 Stakeholders mainly want the information to be easier to find, better tailored to their sector or setting, and available in the formats they prefer. The Care Inspectorate’s new website is expected to help improve this by making guidance easier to locate and navigate.
5.9 Funding has now been confirmed for a final transitional year, ending the SSP on 31 March 2027. Activity during this period will focus on embedding and sustaining implementation of the Act. This includes continuing to support all stakeholders to apply the HCSA guiding principles and statutory duties. Work will also involve maintaining and updating guidance and legacy resources, with a stronger emphasis on clear signposting and sector‑specific packaging. Targeted expertise and support will be provided where evidence shows there is still uncertainty or variation in understanding.
5.10 A key priority during the transitional year will be to strengthen compliance intelligence through annual returns and targeted analytical insight, so that reporting and assurance activity is based on a clear understanding of what is being recorded and where risks persist.
5.11 Engagement with LAs and IAs will also consider compliance and risk management in relation to their HCSA reporting duties with scope to refine the approach to reporting templates and prompts where this would improve clarity and comparability.
5.12 Two longer-term considerations remain relevant throughout the transitional year.
• Sustained progress will continue to be shaped by workforce capacity constraints so support that is practical, proportionate, and low burden is likely to remain most effective.
• Implementation is shaped by interdependencies across the whole system. This includes providers, commissioners, and the Care Inspectorate’s regulatory and assurance activity. Delivery in the final transitional year will therefore need to complement business‑as‑usual activity, annual reporting cycles, and available data.